
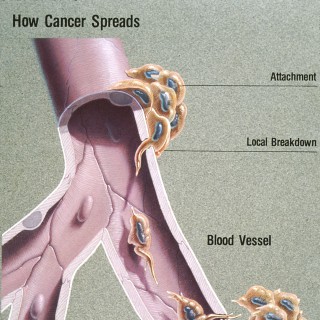
Spread of a disease inside a body
POPULARITY
Categories

368 episodes with metastatic

58 episodes with metastatic

123 episodes with metastatic

39 episodes with metastatic

21 episodes with metastatic

19 episodes with metastatic

26 episodes with metastatic

23 episodes with metastatic

33 episodes with metastatic

32 episodes with metastatic

31 episodes with metastatic

17 episodes with metastatic

19 episodes with metastatic

16 episodes with metastatic

15 episodes with metastatic

13 episodes with metastatic

22 episodes with metastatic

13 episodes with metastatic

13 episodes with metastatic

10 episodes with metastatic

13 episodes with metastatic

8 episodes with metastatic

12 episodes with metastatic

11 episodes with metastatic

12 episodes with metastatic

13 episodes with metastatic

14 episodes with metastatic

10 episodes with metastatic

8 episodes with metastatic

21 episodes with metastatic

9 episodes with metastatic

13 episodes with metastatic

10 episodes with metastatic

11 episodes with metastatic

17 episodes with metastatic

6 episodes with metastatic

9 episodes with metastatic

9 episodes with metastatic

9 episodes with metastatic

5 episodes with metastatic

9 episodes with metastatic

10 episodes with metastatic

9 episodes with metastatic

10 episodes with metastatic

12 episodes with metastatic

10 episodes with metastatic

3 episodes with metastatic

11 episodes with metastatic

5 episodes with metastatic

5 episodes with metastatic

6 episodes with metastatic

6 episodes with metastatic

8 episodes with metastatic

5 episodes with metastatic
In today's episode, we spoke with Kim A. Reiss Binder, MD, about the August 2026 FDA approval of daraxonrasib (Rasonque) for the treatment of adult patients with metastatic pancreatic adenocarcinoma who have received at least 1 prior systemic therapy or are not candidates for multi-agent systemic therapy. Dr Reiss Binder is the assistant program director of the Hematology/Oncology Fellowship Program and an associate professor of medicine (hematology-oncology) at the Hospital of the University of Pennsylvania in Philadelphia.In our exclusive interview, Dr Binder discussed the significance of this approval, key efficacy data from the pivotal phase 3 RASolute 302 trial (NCT06625320), and the importance of continuing to build off of treatment advances to drive clinical research and improve patient outcomes in this field.

What does a urologist actually need to know to confidently manage advanced prostate cancer in the clinic? On this episode of BackTable Urology, host Dr. Ruchika Talwar interviews Dr. Kristen Scarpato, director of the advanced prostate cancer clinic at Vanderbilt University Medical Center, and Dr. Jason Hafron, chief medical officer of the Michigan Institute of Urology. They break down how the landscape has shifted, why more patients stay in urology for treatment, and how to select and monitor therapy based on disease state, comorbidities, and patient goals. --- Get the BackTable apphttps://www.backtable.com/app --- This podcast is supported by Bayer https://www.bayer.com --- Timestamps 00:00 - Introduction02:41 - Shift to Urology-Led Advanced Prostate Management07:07 - Sorting Therapies by Disease State10:33 - Treatment Intensification and Doublet Therapy17:54 - ARPI Selection and the Four Ps Framework25:46 - Managing Financial Toxicity29:30 - Monitoring, Labs, and Imaging34:11 - Red Flags and Comanagement36:49 - When to Refer to Medical Oncology41:11 - Future Directions and Practice Economics46:33 - Closing Remarks --- More about this episode The discussion covers sorting therapies by disease state rather than drug class, doublet and triplet intensification, the nuances of choosing between abiraterone, enzalutamide, apalutamide, and darolutamide, and Dr. Hafron's “four Ps” framework for drug selection. Dr. Scarpato addresses financial toxicity, surveillance protocols, and red flag symptoms. Both guests share their referral triggers for medical oncology, approaches for oligometastatic disease and metastasis-directed therapy, and practical tips for running an advanced prostate cancer clinic. --- Resources Advanced Prostate Cancer: AUA/SUO Guidelinehttps://www.auanet.org/guidelines-and-quality/guidelines/advanced-prostate-cancer Trial Design and Objectives for Patients With Prostate Cancer: Recommendations From the Prostate Cancer Working Group 4 (JCO)https://ascopubs.org/doi/10.1200/JCO-25-02834 ARACOG (AFT-47): Darolutamide vs Enzalutamide and Cognitive Function, ClinicalTrials.gov NCT04335682https://clinicaltrials.gov/study/NCT04335682 ARASENS: Darolutamide and Survival in Metastatic, Hormone-Sensitive Prostate Cancer (NEJM)https://www.nejm.org/doi/full/10.1056/NEJMoa2119115 PSMAddition: 177Lu-PSMA-617 Plus Standard of Care in mHSPC, ClinicalTrials.gov NCT04720157https://clinicaltrials.gov/study/NCT04720157 Medicare Plan Finder, referenced on air for comparing Part D out-of-pocket drug costshttps://www.medicare.gov/plan-compare/ --- BackTable Urology is the go-to podcast for urologists, urologic oncologists, and urogynecologists. Download the free BackTable app to get early access to new episodes, cases, and courses curated by physicians in your specialty. ► https://www.backtable.com/app
Welcome to the Komen Health Equity Revolution series on Real Pink — where patients, advocates, researchers and community partners come together to talk honestly about what's standing in the way of breast health equity and what we're doing to change it. I'm your host, Adam Walker. This month is Hispanic Heritage Month, and we're honoring it by talking about something a lot of young women don't expect to be part of their story this early: Needing to have a mammogram as a young adult. Our guest today is Yaleska Sosa, a senior at Northwestern University studying biological sciences and global health, and a Komen College Ambassador. During a routine appointment, doctors found a mass and referred her for a mammogram — an experience that, combined with her family's history of cancer, turned a scare into a mission: making sure other young women, especially in the Hispanic/Latino community, have the information she wishes she'd had. Yaleska, welcome to Real Pink. Takeaway Breast cancer can affect people at any age, even those who consider themselves healthy. Knowing your body can help you notice changes and take action sooner. Family history and cultural experiences can shape how people understand their health. Sharing accessible health information can help young people feel more informed and empowered. One conversation or small act of awareness can have an impact beyond what we may ever see. Chapters 00:01 — Yaleska's unexpected mammogram 06:00 — Deciding whether to tell her mom 06:47 — Knowing your body and your culture 09:39 — Discovering the impact of breast cancer 13:55 — Encouraging young women to know their bodies Learn more at realpink.komen.org and komen.org Real Pink, by Susan G. Komen, shares real stories and expert insights to support people navigating breast cancer, from diagnosis through survivorship.
Featuring perspectives from Dr David W Cescon, including the following topics: Clinical treatment of BRCA-mutated metastatic triple-negative breast cancer (0:00) CNS activity of TROP2-directed antibody-drug conjugates (5:36) Autoimmune considerations with immunotherapy (10:09) Treatment of oligoprogressive advanced breast cancer (17:31) CME information and select publications
When we think about breast cancer, many of us still picture someone much older. But the reality is that young women can—and do—face this diagnosis, even when breast cancer is the furthest thing from their minds. Today's guest was just 35 years old when her life changed and she suddenly found herself navigating treatment decisions while raising 3 young children. Amanda Lutricuso's story is a powerful reminder that you're never too young to pay attention to your body and to speak up when something is wrong. Cancer may have changed the course of her life, it also changed her perspective on what matters most. Key Takeaways Breast cancer can happen at any age, even without family history. A strong family support system can help manage treatment. Young women should advocate for themselves when something feels wrong. Chapters 00:01:19 Finding the lump 00:03:22 Processing the diagnosis 00:08:07 Balancing treatment and motherhood 00:12:29 Chasing every dream 00:16:07 Advocating for your health Learn more at realpink.komen.org and komen.org Real Pink, by Susan G. Komen, shares real stories and expert insights to support people navigating breast cancer, from diagnosis through survivorship.
Featuring perspectives from Dr David W Cescon, including the following topics: First-line treatment of metastatic triple-negative breast cancer (mTNBC) in patients not eligible for immunotherapy (0:00) First-line treatment of mTNBC in patients eligible for immunotherapy (12:05) Adverse events (19:39) CME information and select publications
Featuring perspectives from Dr Alexandra Drakaki, including the following topics: Case: A man in his early 80s with bladder cancer and metastatic progression in the viscera and lymph nodes receives enfortumab vedotin (EV) with pembrolizumab — Part 1 (0:00) Case: A man in his early 80s with metastatic bladder cancer achieves a complete response with EV/pembrolizumab therapy but develops gastrointestinal toxicity — Part 2 (5:37) Case: A man in his early 50s with metastatic bladder cancer receives second-line EV monotherapy intermittently (15:09) Case: A woman in her mid 60s with bladder cancer and a history of rheumatoid arthritis develops oligometastatic progression in the lung and receives EV monotherapy (21:03) Case: A man in his mid 80s with HER2-positive (IHC 3+) metastatic bladder cancer receives trastuzumab deruxtecan and develops ground glass opacities in his lungs concerning for pneumonitis (30:43) CME information and select publications
Featuring perspectives from Dr Alexandra Drakaki, including the following topics: Case: A man in his late 70s with diabetes and metastatic bladder cancer achieves radiographic response with enfortumab vedotin (EV) and pembrolizumab but develops uncontrolled hyperglycemia (0:00) Case: A man in his early 70s with muscle-invasive bladder cancer receives adjuvant nivolumab and experiences metastatic progression after 9 cycles of therapy (6:23) Case: A woman in her early 70s with Lynch syndrome and metastatic upper tract bladder cancer receives EV/pembrolizumab and develops myasthenia gravis (13:59) Case: A woman in her late 40s with FGFR3 mutant metastatic bladder cancer receives erdafitinib and experiences rising serum phosphate levels (20:04) CME information and select publications

This episode is sponsored by Gilead Sciences. Gilead had no involvement or input in the podcast content. Gilead is working to transform how cancer is treated. We are innovating with next-generation therapies, combinations, and technologies to deliver improved outcomes for people with cancer. From antibody drug conjugates and small molecules to cell therapy-based approaches, our portfolio and pipeline assets are creating new possibilities for people with cancer.Recorded on location at the San Antonio Breast Cancer Symposium, December 2025.Metastatic triple-negative breast cancer remains the breast cancer subtype with the fewest targetable biomarkers and the shortest treatment algorithm. When a trial reports a double-digit progression-free survival in the first-line setting, it is worth understanding what that actually changes and how the trial was designed with patient outcomes at the center.This episode was recorded in December 2025, before regulatory action. On June 24, 2026, the FDA approved sacituzumab govitecan-hziy for two first-line indications in triple-negative breast cancer: as a single agent for adults with unresectable locally advanced or metastatic TNBC who are not candidates for PD-1 or PD-L1 inhibitor-based therapy supported by ASCENT-0, and in combination with pembrolizumab for adults whose tumors express PD-L1 with a CPS of 10 or greater supported by ASCENT-04. Janice's speculation in this episode about how PD-L1 status might factor into the guidelines has since been answered by the label.ASCENT-04/KEYNOTE-D19 NCT05382286 was a phase 3, open-label, randomized trial of 443 patients with previously untreated locally advanced unresectable or metastatic TNBC whose tumors expressed PD-L1 at a CPS of 10 or greater by the 22C3 assay. Participants were randomized 1:1 to sacituzumab govitecan plus pembrolizumab or to physician's choice of chemotherapy plus pembrolizumab. Patients in the control arm with centrally confirmed progression were offered crossover to sacituzumab govitecan.0:00 Live from the San Antonio Breast Cancer Symposium0:30 The METAvivor ribbon and what the pink ribbon leaves out1:35 Diagnosed in 2016 with a median overall survival of 9 to 15 months2:26 Nine years later3:20 From pediatric nursing to research advocacy4:30 What has changed since 2017, and what has not5:26 2011: when chemotherapy was the only option5:55 On not knowing a relevant clinical trial existed6:47 Why metastatic TNBC still has no maintenance therapy7:25 What first-line treatment looks like today8:25 Inside ASCENT-049:09 Progression-free survival, defined9:59 Why a double-digit PFS is notable in this subtype11:20 Why each subsequent line of treatment works for less time11:52 How many patients never reach second line12:50 The case for a stronger first-line option13:21 Crossover design, and why it matters to patients14:33 What crossover means in a randomized trial15:56 Patient advocates in clinical trial design18:59 Quality of life versus quantity of life21:48 Rapid fire: metastatic breast cancer and metastatic TNBC23:06 Rapid fire: first line, second line, progression-free survival24:00 Rapid fire: immunotherapy and antibody-drug conjugates24:59 Advice for the newly diagnosed26:04 What she wants next: a biomarker26:52 On ADCs, tolerability, and the need for novel targetsJanice Cowden, RN is a research patient advocate living with metastatic triple-negative breast cancer. She practiced as a registered nurse for approximately 22 years, primarily in pediatrics, and later worked as a pharmaceutical sales representative. She was diagnosed with stage I triple-negative breast cancer in 2011 and with metastatic disease in 2016, and completed the Living Beyond Breast Cancer advocacy training program in 2017.This podcast is intended for educational and informational purposes only and should not be considered medical advice.
Technology is rapidly changing the world around us – and the same is true in women's health. Artificial Intelligence holds enormous promise in understanding risk, detecting cancers earlier and improving treatment options and outcomes for breast cancer patients – but how do we get there and what should we be aware of along the way? Today we're welcoming Jillian Wright, the CEO of Onsite Women's Health, the leading provider of convenient, in-office breast health imaging services across the U.S., and Jane Perlmutter, a survivor of multiple cancers and devoted member of Susan G. Komen Advocates in Science program, which brings the patient voice to scientific research and clinical decisions. Takeaways AI can improve breast cancer detection and diagnosis AI can make breast imaging more consistent and effective Patients need a voice in how AI is used in healthcare AI must be developed with diversity, privacy and equity in mind Personalized care could reshape the future of breast cancer screening Chapters 00:00 — The promise of AI in breast health 05:12 — Understanding breast cancer risk 10:29 — How AI is transforming breast imaging 19:28 — The concerns around AI in healthcare 24:40 — The future of AI and cancer care Learn more at realpink.komen.org and komen.org Real Pink, by Susan G. Komen, shares real stories and expert insights to support people navigating breast cancer, from diagnosis through survivorship.
Two Onc Docs, hosted by Samantha A. Armstrong, MD, and Karine Tawagi, MD, is a podcast dedicated to providing current and future oncologists and hematologists with the knowledge they need to ace their boards and deliver quality patient care. Dr Armstrong is a hematologist/oncologist and assistant professor of clinical medicine at Indiana University Health in Indianapolis. Dr Tawagi is a hematologist/oncologist and assistant professor of clinical medicine at the University of Illinois in Chicago.In this episode, OncLive On Air® partnered with Two Onc Docs to deliver a comprehensive, board-focused review of metastatic non–small cell lung cancer (NSCLC) diagnosis and management for 2026, reflecting the rapidly expanding treatment landscape that is growing to include chemotherapy, immunotherapy, and targeted agents.The discussion began with molecular workup, emphasizing the importance of conducting upfront multigene next-generation sequencing plus PD-L1 testing by immunohistochemistry (IHC) for all nonsquamous disease, with HER2 and c-MET IHC now part of routine evaluation. Drs Armstrong and Tawagi stressed that circulating tumor DNA complements but does not replace tissue biospy, and that a targetable driver generally prompts the initiation of first-line targeted therapy, except in the case of KRAS G12C and NRG1 fusions.Regarding EGFR-mutated disease, they reviewed 3 category 1 first-line options: osimertinib (Tagrisso) monotherapy, osimertinib plus chemotherapy, and amivantamab (Rybrevant) plus lazertinib (Lazcluze), cautioning against overlapping immunotherapy. They detailed post-osimertinib resistance testing and EGFR exon 20 insertions, then addressed ALK, ROS1, BRAF V600E, RET, MET exon 14, NTRK, and NRG1 alterations, noting preferred agents and characteristic toxicities, such as lorlatinib (Lorbrena)–associated hyperlipidemia.Drs Armstrong and Tawagi also covered HER2-directed therapies, including fam-trastuzumab deruxtecan-nxki (Enhertu), as well as antibody-drug conjugates for EGFR-mutated and c-MET–high disease. For driver-negative disease, they stratified first-line therapy by PD-L1 status and histology, discussing immunotherapy monotherapy, chemoimmunotherapy, and dual checkpoint blockade, before reviewing second-line options for patients with or without prior immunotherapy.
This week's episode focuses on metastatic non-small cell lung cancer - the quickly growing and changing systemic therapy landscape, including traditional chemotherapy, immunotherapy, and targeted agents. Since our last recording the number of FDA-approved targeted drugs has significantly expanded.

Send us Fan MailWelcome to the Simply Oncology Podcast. Today we are focusing in on the prostate cancer trial called INTENSIFY. This is a trial where we will look at intensifying metastatic prostate cancer patients.Those patients established on combination LHRHa and ARPi therapy could then be randomised at 6months to adding chemotherapy or not if they don't have an optimal PSA tumour marker improvement.We have brought the wonderful Professor Simon Crabb, and Dr Sarah Chamberlain from the oncology team at Southampton. They are part of the leadership team for the trial. This trial is already running in some centres and we discuss why it is happening and how it would be delivered.
This week the Head and Neck series turns to what happens when local therapy isn't enough — recurrent, relapsed, and metastatic disease. Using the case of a woman with a laryngeal cancer recurrence, we work through the first and most important question (recurrence versus second primary), the workup and biomarkers that steer therapy, local salvage options, the CPS-driven first-line systemic algorithm, second-line and beyond, the distinct world of nasopharyngeal cancer, oligometastatic disease, and the central role of early palliative and supportive care. As always, if you haven't heard the earlier episodes in this series, start there first.**This episode is sponsored by Primum! Sign up for your free account at primum.co/fellows** Want to review the show notes for this episode and others? Check out our website. Love what you hear? Tell a friend and leave a review on our podcast streaming platforms!Twitter: @TheFellowOnCallInstagram: @TheFellowOnCallListen in on: Apple Podcast, Spotify, and Youtube
The first 30 days after being diagnosed with breast cancer can feel devastating. You're processing a lot of information, dealing with emotions and often trying to figure out what to do next. Joining us on Real Pink's 400th episode today is Jennifer Omholt, a journalist and 24-year cancer survivor who was diagnosed with stage 3 breast cancer when her son was just 16 months old. In the wake of her diagnosis, she desperately searched for something to ease her fear and confusion, but found nothing that offered comfort or clarity. Over the next two decades, she set out to create the resource she wished she'd had, so that no one would need to face the shock of a cancer diagnosis alone. Jennifer is here today to share her story and what helped carry her though her breast cancer experience. Key takeaways: You don't have to solve cancer all at once; focus on the next best step. Finding the right medical team can make a profound difference in your care. Self-advocacy means asking questions, trusting your instincts, and seeking second opinions. Letting others help can ease the emotional and practical burden of cancer. The fear of a diagnosis can fade as you gain knowledge, confidence, and a sense of control. Chapters 00:01:23 — A stage three diagnosis with a 16-month-old son 00:03:25 — Finding ways to manage fear and uncertainty 00:07:57 — The first 30 days after a breast cancer diagnosis 00:09:59 — Building a medical team you can trust 00:15:07 — Why self-advocacy can change your treatment Learn more at realpink.komen.org and komen.org Real Pink, by Susan G. Komen, shares real stories and expert insights to support people navigating breast cancer, from diagnosis through survivorship.

This episode highlights FDA approval of the first-in-class RAS inhibitor daraxonrasib for metastatic pancreatic adenocarcinoma, concerning gaps in cervical cancer screening and HPV vaccination among younger women, and new evidence defining which patients may benefit most from coronary artery calcium scoring alongside the PREVENT cardiovascular risk calculator.
BUFFALO, NY – September 1, 2026 – A new #review was published in Volume 17 of Oncotarget on August 28, 2026, titled “Emerging biomedical imaging applications of tumor-derived extracellular vesicles for premetastatic niche detection: Biological rationale, engineering strategies, and translational challenges.” The review was led by first author Omkar Dhaygude, who is affiliated with Johns Hopkins University. Corresponding authors Franck Housseau and John Michel are affiliated with Johns Hopkins University, with Housseau also affiliated with the Cancer Research Center of Lille in France. Extracellular vesicles (EVs) are membrane-enclosed particles released by cells that transport proteins, lipids, nucleic acids, metabolites, and other molecular cargo. In cancer, tumor-derived extracellular vesicles (TEVs) can influence the tumor microenvironment and distant tissues by promoting processes such as angiogenesis, extracellular matrix remodeling, inflammatory signaling, immune evasion, and stromal reprogramming. Of particular interest is the role of TEVs in establishing premetastatic niches—biological environments in distant organs that become permissive to metastatic cells before overt tumors are detectable. TEVs can carry organ-specific molecular signals, and their surface molecules may influence which tissues they reach. For example, previous experimental research has linked the integrins α6β4 and α6β1 with lung tropism, providing a biological rationale for using TEVs to direct imaging probes toward metastasis-prone organs. This possibility could address an important limitation of conventional cancer imaging. Computed tomography and other anatomical methods are designed primarily to detect established structural lesions, whereas premetastatic niches are characterized by earlier molecular and microenvironmental alterations. The authors therefore examine whether TEV-associated imaging could provide information about metastatic conditioning before conventional imaging can identify overt metastatic lesions. Full press release - https://www.oncotarget.com/news/pr/tumor-derived-extracellular-vesicles-show-promise-for-earlier-detection-of-metastatic-risk/ DOI - https://doi.org/10.18632/oncotarget.28916 Correspondence to - Franck Housseau - fhousse1@jhmi.edu, and John Michel - jmiche14@jhmi.edu Abstract video - https://www.youtube.com/watch?v=0zygNvj4_YY Sign up for free Altmetric alerts about this article - https://oncotarget.altmetric.com/details/email_updates?id=10.18632%2Foncotarget.28916 Subscribe for free publication alerts from Oncotarget - https://www.oncotarget.com/subscribe/ Keywords - cancer, lung metastases, cancer imaging, theranostic, premetastatic niches, extra-cellular vesicles To learn more about Oncotarget, please visit https://www.oncotarget.com and connect with us: Facebook - https://www.facebook.com/Oncotarget/ X - https://twitter.com/oncotarget Instagram - https://www.instagram.com/oncotargetjrnl/ YouTube - https://www.youtube.com/@OncotargetJournal LinkedIn - https://www.linkedin.com/company/oncotarget Pinterest - https://www.pinterest.com/oncotarget/ Reddit - https://www.reddit.com/user/Oncotarget/ Spotify - https://open.spotify.com/show/0gRwT6BqYWJzxzmjPJwtVh MEDIA@IMPACTJOURNALS.COM
Metastatic breast cancer cannot be cured but it can be treated. Treatment focuses on disease management while maintaining the best possible quality of life. The unfortunate reality is that a treatment will only work for so long, then another one is needed. Joining us today are two women living with metastatic breast cancer who are sharing their experiences, living one treatment to the next. They are tireless advocates for research and the breakthroughs that will ensure their next treatment is available, when they need it. They're sharing how they live life to the fullest and manage their day-to-day care. Key Takeaways It's important to find hope while living treatment to treatment Recognize the physical and emotional toll of treatment, even when you look well Advocate for research, clinical trials, and discoveries that lead to better treatments Live in the present, prioritize quality of life, and give yourself grace Chapters 00:00 — Living with metastatic breast cancer 03:25 — The reality of treatment after treatment 07:45 — The emotional weight of uncertainty 13:23 — Why metastatic breast cancer research matters 26:34 — Living in the present and finding hope Learn more at realpink.komen.org and komen.org Real Pink, by Susan G. Komen, shares real stories and expert insights to support people navigating breast cancer, from diagnosis through survivorship.
Featuring perspectives from Prof Peter Schmid and Dr Melinda Telli, including the following topics: Introduction: TROP2-Targeting Antibody-Drug Conjugates (ADCs) for Metastatic Triple-Negative Breast Cancer (0:00) First-Line Therapy (PD-L1 Negative) (6:53) First-Line Therapy (PD-L1 Positive) (23:40) Second-Line Therapy (Sequencing) (34:08) Adverse Events with TROP2-Targeting ADCs (43:43) CME information and select publications
What happens when your life changes in an instant, and then, just when you think you're beginning to rebuild, you're faced with another life-altering diagnosis? Shannon Michelle knows that experience firsthand. After a devastating motorcycle accident left her in a coma with a traumatic brain injury, Shannon had to relearn how to walk, read, speak and navigate a life she no longer remembered. Then, during her recovery, she was diagnosed with breast cancer. Today, Shannon joins us to talk about her breast cancer experience, the emotional realities of healing, and how an unimaginable series of events changed the way she sees her life. Key Takeaways Stay present, especially when life feels overwhelming Self-care is essential to recovery Accepting a new reality can be empowering Let go of what you cannot control Give yourself permission to be the best version of yourself today Chapters 00:00 — Surviving a devastating accident 04:30 — A breast cancer diagnosis 07:57 — The PATCH framework for healing 16:50 — Accepting a new reality 23:50 — Letting go of control Learn more at realpink.komen.org and komen.org Real Pink, by Susan G. Komen, shares real stories and expert insights to support people navigating breast cancer, from diagnosis through survivorship.
This episode is sponsored by Gilead Sciences. Gilead had no involvement or input in the podcast content. Gilead is working to transform how cancer is treated. We are innovating with next-generation therapies, combinations, and technologies to deliver improved outcomes for people with cancer. From antibody drug conjugates and small molecules to cell therapy-based approaches, our portfolio and pipeline assets are creating new possibilities for people with cancer.Dr. Sara Tolaney, Chief of the Division of Breast Oncology at Dana-Farber Cancer Institute, returns to Patient From Hell to explain the ASCENT-04/KEYNOTE-D19 study, the phase 3 trial she led as principal investigator, and what it changes for people living with metastatic triple-negative breast cancer.For years, the most effective drugs for metastatic TNBC were only available after first-line chemotherapy had already failed. The problem, as Dr. Tolaney puts it plainly, is that many patients never reach a second line of treatment at all. ASCENT-04 asked whether moving an antibody-drug conjugate to the front, paired with immunotherapy, would change that. Median progression-free survival improved from 7.8 months to 11.2 months, and treatment responses lasted significantly longer.UPDATE: Since this recorded conversation, the FDA has acted on the data discussed in this episode. On May 22, 2026, Datopotamab Deruxtecan was approved for first-line metastatic TNBC in patients who are not candidates for immunotherapy. On June 24, 2026, Sacituzumab Govitecan was approved for first-line use both as a single agent and in combination with pembrolizumab for PD-L1-positive disease (CPS ≥10). Consult with your care team for the most recent indications and availability of these treatment options.00:00 The trial that moves the best drugs first 00:31 Welcome back, Dr. Sara Tolaney 00:40 What ASCENT-04 set out to solve 02:00 Why many patients never reach second-line treatment 02:50 What PD-L1 status means for your treatment 04:12 The result: 7.8 to 11.2 months 05:29 What is an antibody-drug conjugate (ADC)? 06:33 Why TROP-2 is the target in triple-negative breast cancer 07:24 How immunotherapy works: taking the brakes off the T cell 09:01 Who was eligible for the trial 10:05 What "controlling" cancer actually means 11:44 Progression-free survival vs. duration of response 13:37 Dr. Tolaney reconsiders: what ASCENT-03 showed 15:51 How trial data reaches your oncologist's office 18:21 The testing checklist after a metastatic diagnosis 19:59 First-line treatment options today 22:27 The new paradigm: ADCs as the first-line backbone 23:51 What comes second line 25:29 Why tumor sequencing matters: somatic BRCA, TMB, trials 27:24 Twenty years of change in triple-negative breast cancer 29:28 Advice for a newly diagnosed patientSara M. Tolaney, MD, MPH is Chief of the Division of Breast Oncology and Associate Director of the Susan F. Smith Center for Women's Cancers at Dana-Farber Cancer Institute, and Associate Professor of Medicine at Harvard Medical School. She trained at Princeton University, UC San Francisco, Johns Hopkins University, and Dana-Farber Cancer Institute, and holds a Masters in Public Health (MPH) from Harvard University. She serves on the National Cancer Institute (NCI) Breast Cancer Steering Committee and is Vice Chair for Late-Stage Development in Breast Cancer for the Alliance for Clinical Trials in Oncology. She was principal investigator of ASCENT-04.
Featuring perspectives from Prof Yohann Loriot, including the following topics: Case: A man in his early 80s with metastatic urothelial bladder cancer (mUBC) receives enfortumab vedotin (EV)/pembrolizumab but experiences immune-related adverse events requiring steroids and then develops neuropathy due to EV — Nazli Dizman, MD (0:00) Case: A man in his early 70s with diabetes who received adjuvant nivolumab for FGFR3-mutant metastatic urothelial cancer receives first-line EV monotherapy and experiences hyperglycemia and cancer progression, then receives erdafitinib and experiences elevated phosphase, Grade 2 diarrhea and stomatitis and eventual disease progression — Jacqueline T Brown, MD (7:00) Case: A man in his late 80s with mUBC receives first-line EV/pembrolizumab and develops pneumonitis — Fern Anari, MD (17:40) CME information and select publications
Bret Miller was 17 when he first felt a lump behind his nipple. For seven years, providers told him it was calcium buildup or that it would go away on its own. It didn't. At 24, Bret was diagnosed with Stage 1 breast cancer — a disease most people, including many of the doctors he saw along the way, don't associate with men at all.In this episode, Bret joins his oncologist, Dr. Priyanka Sharma of The University of Kansas Cancer Center, to unpack why male breast cancer is so often missed or overlooked by so many health care providers — and why most men have never been told what normal breast tissue looks or feels like for them in the first place. Together, they talk about what needs to change in clinical training and patient conversations, and what self-advocacy looks like when the system isn't built to catch what you're describing. This episode is part of the Komen Health Equity Revolution podcast series, which centers the lived experience of communities too often overlooked in breast cancer awareness and care — including men. 5 Key Takeaways Men need to know the signs and symptoms of breast cancer A persistent change in one breast should be investigated Nipple discharge can be a warning sign of breast cancer Patients should advocate for themselves and seek second opinions Healthcare providers should take concerning breast changes seriously Chapters 03:10 Bret's Seven-Year Journey to a Diagnosis 10:55 Why Male Breast Cancer Gets Missed 15:09 Knowing What Is Normal for Men 17:11 Turning a Diagnosis Into Advocacy 24:39 How Healthcare Providers Can Close the Gap Learn more at realpink.komen.org and komen.org Real Pink, by Susan G. Komen, shares real stories and expert insights to support people navigating breast cancer, from diagnosis through survivorship.

Matt Smith, 42, metastatic prostate cancer, Wilmington, NC, with Michael Serzan, Medical Oncologist, Lank Center for Genitourinary Oncology, Dana-Farber Cancer Institute
Featuring perspectives from Prof Yohann Loriot, including the following topics: Case: A man in his early 80s with Parkinson disease and a history of renal transplant presents with metastatic urothelial bladder cancer (UBC) and receives first-line enfortumab vedotin (EV) with a good response but develops neuropathy and skin toxicity — Jacqueline T Brown, MD (0:00) Case: A man in his early 90s with excellent PS and locally advanced UBC receives EV and pembrolizumab as palliative treatment, develops neuropathy, discontinues the EV and continues pembrolizumab with no toxicity — Catherine Fahey, MD, PhD (12:01) Case: A woman in her late 50s with metastatic UBC receives EV with pembrolizumab on a clinical trial and experiences a response but develops diarrhea and pruritus — Fern Anari, MD (21:43) CME information and select publications
Metastatic osteosarcoma remains a major clinical challenge, highlighting the need to better understand the molecular mechanisms that drive disease progression. In this talk, Moreno will present the use of an in vivo CRISPR interference (CRISPRi) screen to identify genes that promote osteosarcoma progression. She will focus on KLF5, a transcription factor that emerged as a key regulator in our studies, and discuss its potential as a therapeutic target for osteosarcoma.Marta Roman Moreno, PhD, is a postdoc fellow in the Sweet-Cordero Lab at UCSF. She has a BSc in Biochemistry from the University of Granada in Spain, and an MSc and PhD in Biomedical Research from the University of Navarra (Spain). The key focus of her work is to define key regulators of metastasis in osteosarcoma and determine the vulnerabilities that can diminish the survival of metastatic cells. Using mouse models, cell lines derived from patient samples (PDXs) and pooled in vivo CRISPR screens, she has been able to identify several potential genetic vulnerabilities in the context of metastatic osteosarcoma.
Breast cancer treatment has a beginning and an end, but healing is often a much longer journey. Today, we are joined by Katie Wasserman, a remarkable mother of four who shares how trusting her instincts and advocating for herself led to her breast cancer diagnosis. She will talk about navigating treatment decisions, the impact it had on her body, and the physical and emotional healing that continues today into survivorship. From managing the fears that linger after treatment ends to intentionally choosing a life focused on thriving instead of simply surviving, Katie's story is a powerful reminder that no one knows your body better than you do. Key Takeaways Trust your instincts when something feels wrong Self-advocacy can lead to life-saving care Asking for help strengthens recovery Small daily habits support healing and resilience Survivorship is about thriving, not just surviving Chapters 00:00 – Trusting your instincts 05:09 – The power of self-advocacy 07:51 – Recovery, support, and staying active 15:04 – Sharing the journey through Instagram 18:27 – Thriving beyond survivorship Learn more at realpink.komen.org and komen.org Real Pink, by Susan G. Komen, shares real stories and expert insights to support people navigating breast cancer, from diagnosis through survivorship.
When multiple loved ones are diagnosed with breast cancer within a short period of time, it can leave you wondering if, and when, it might become part of your own story. Megan May knew her family history meant that she was at greater risk of developing breast cancer. She prepared as best she could and underwent regular screenings. However, her diagnosis at age 40 still came as a shock because there are some things that no one can fully prepare you for. Megan is here today to share her story - how a series of family diagnoses prompted her to begin early screening, what it was like to hear the words no one wants to hear, and the physical and emotional challenges that followed. We'll talk about how why giving back through fundraising has become such an important part of her mission and how her family supports each other through it all. Key Takeaways Family history can help identify when earlier screenings are needed Early detection can allow cancer to be caught and treated quickly Supporting someone with cancer starts with simply being present Knowing your normal and getting screened can save lives Chapters 00:00 – Megan's family history with breast cancer 02:20 – Starting early screenings 04:04 – Megan's diagnosis and treatment journey 09:39 – Finding strength through movement and survivorship 14:46 – Supporting family and advocating for early detection Learn more at realpink.komen.org and komen.org Real Pink, by Susan G. Komen, shares real stories and expert insights to support people navigating breast cancer, from diagnosis through survivorship.
Highlights from the PER® CME activity "From Trials to the Clinic ‒ Incorporating New Advances in Metastatic TNBC" — this podcast is not certified for credit. To participate in the full accredited activity and earn CME credit, use the link below.In this podcast, experts William Gradishar, MD, FASCO, FACP; and Kamel Abou Hussein, MD; discuss optimizing first-line treatment selection in metastatic triple-negative breast cancer (TNBC) with emerging antibody-drug conjugates (ADCs) and biomarker-guided strategies.Earn CME credit by completing the full accredited activity (available through July 31, 2027): https://www.gotoper.com/courses/from-trials-to-the-clinic-incorporating-new-advances-in-metastatic-tnbcThis podcast, including the narration, was developed by PER® (Physicians' Education Resource®, LLC) editorial staff from the full online CME activity developed with these faculty. The narration was voiced by a PER staff member or by an AI tool. The podcast contains no product advertising. The full activity is supported by an educational grant from Gilead Sciences, Inc.This content is for educational purposes only and is not a substitute for the independent clinical judgment of a health care professional. Faculty may discuss investigational or off-label uses; consult prescribing information for any products discussed.
In today's episode, we spoke with Marlana M. Orloff, MD. Dr Orloff is the Alexander & Johnston Family Endowed Clinical Director in Uveal Melanoma, and associate professor at Thomas Jefferson University Hospital in Philadelphia, Pennsylvania. In our exclusive interview, Dr Orloff discussed the distinct biology of uveal melanoma and why it has historically resisted systemic treatment. Unlike cutaneous melanoma, which carries a high tumor mutational burden and responds robustly to immune checkpoint inhibitors, uveal melanoma sits at the opposite end of the spectrum with low mutational burden, a predominantly liver-metastatic pattern, and an immune-tolerant microenvironment that renders traditional immunotherapy largely ineffective.She provided context on the treatment landscape for patients with HLA-A*02:01–negative metastatic uveal melanoma prior to the phase 2/3 OptimUM-02 trial (NCT05987332), noting that this population had limited options: liver-directed therapies such as percutaneous hepatic perfusion, off-label immune checkpoint inhibitor combinations, or clinical trial enrollment.Dr Orloff then walked through the design and efficacy findings of the trial, which evaluated the combination of darovasertib, an oral PKC inhibitor, plus crizotinib (Xalkori), a MET inhibitor, vs investigator's choice in treatment-naive, HLA-A*02:01–negative patients. The combination demonstrated a median progression-free survival of 6.9 months vs 3.1 months with investigator's choice, with an objective response rate of 37.1% compared with under 5.8% in the control arm. She highlighted the clinical significance of the complete responses observed while noting that overall survival data from the phase 3 portion of the trial remain pending.The discussion also addressed the growing complexity of treatment sequencing as more options emerge, including tebentafusp-tebn (Kimmtrak) for HLA-A*02:01–positive patients, liver-directed and combination approaches, and the investigational TCR-engineered T-cell therapy anzutresgene autoleucel targeting PRAME. Dr Orloff emphasized that in the absence of head-to-head comparisons, sequencing decisions will increasingly be shaped by patient logistics, toxicity profiles, and access to specialized treatment centers.

For this Managed Care Cast episode, The American Journal of Managed Care® (AJMC®) spoke with Anuraag R. Kansal, PhD, who leads health economics research at GRAIL, about his study, “State Medicaid Budgetary Implications of New Cancers," published in the July 2026 issue; it examined how new cancer diagnoses affected state Medicaid budgets. He conducted the study with Amanda C. Chen, PhD, of the USC Mann School of Pharmacy and Pharmaceutical Sciences, and David C. Grabowski, PhD, of Harvard Medical School. Kansal explained to AJMC that despite Medicaid's younger population, cancer remains the third-largest source of program spending. Most existing research had focused on commercial and Medicare populations rather than Medicaid specifically. Consequently, using de-identified CMS claims data, he and his team identified new cancer diagnoses, defined as no prior cancer evidence in the preceding 6 months, and compared spending, hospitalizations, and emergency department use between metastatic and non-metastatic cases. Kansal highlighted the core finding, which was that metastatic diagnoses were associated with significantly higher spending than non-metastatic diagnoses across most cancer types. Notably, health care utilization patterns were consistent between fee-for-service and capitated Medicaid states, suggesting that cost drivers stemmed from the disease itself, particularly the shift to systemic therapies once cancer spread, rather than from program administration models. Kansal pointed to the 4 cancer screenings recommended by the US Preventive Services Task Force, namely lung, breast, colorectal, and cervical, as opportunities to reduce late-stage diagnoses and their associated costs while noting that cancers without established screening protocols presented a distinct policy challenge. On balancing innovative treatment access with cost sustainability, he emphasized that Medicaid's state-by-state administration means that no single policy solution applied universally. Still, Kansal emphasized that earlier detection could offer states greater financial flexibility to support innovative therapies for patients with true clinical need. “Intervening earlier is one of the opportunities we might have to really make a difference,” he concluded.
Disability and breast cancer intersect in more than one direction. Some people develop long-term effects like lymphedema, neuropathy or cognitive changes because of treatment — effects recognized as disabilities under the Americans with Disabilities Act. Others are already living with a disability, of any kind, when a breast cancer diagnosis enters the picture. This July, in recognition of Disability Pride Month, Krista Park Berry, Director of Susan G. Komen's Breast Care Helpline, returns to Real Pink to talk about how the Helpline supports people through their breast health experience no matter when their disability started, and what that support looks like for women of color in particular. Key takeaways No two disability experiences are the same Disability can exist before or develop after breast cancer treatment The Komen Breast Care Helpline provides personalized support and resources Accessible, whole-person care improves quality of life and health outcomes Chapters 00:00 – Understanding disability and breast cancer 02:08 – Treatment-related disabilities and ADA protections 06:26 – Supporting people living with metastatic breast cancer 08:11 – Navigating breast cancer with a pre-existing disability 12:11 – Health equity, women of color, and closing care gaps 13:36 – Why asking for help can change everything
Artificial Intelligence is buzzy. There's a lot about it in the news and a lot we think we understand about how to use it and a lot we may not fully understand. But the promise it holds is tremendous, and today we're going to learn a little more about how it could benefit breast cancer research and patient care in the near future. Drs. Charles Perou at UNC Chapel Hill and Erika Crosby at Duke University are two very accomplished breast cancer researchers who are joining us today to share their perspectives on using AI now and in the future. Key takeaways AI is improving breast cancer screening and diagnosis. Researchers are using AI to save time on coding, writing, and data analysis. AI can help match patients to clinical trials more effectively. Human expertise is still needed to verify AI-generated results. AI has the potential to accelerate research and improve patient care. Chapters 00:00 — Introduction to AI in Breast Cancer Research 02:53 — Ethical Considerations and Responsible AI Use 04:33 — Current Clinical Applications of AI 08:12 — How Researchers Are Using AI in the Lab 11:17 — AI Limitations, Mistakes, and Critical Thinking 17:23 — The Future of AI-Assisted Cancer Research Learn more at realpink.komen.org and komen.org Real Pink, by Susan G. Komen, shares real stories and expert insights to support people navigating breast cancer, from diagnosis through survivorship.
We know that clinical trials are a critical lifeline, offering new ways to prevent, detect, diagnose and treat breast cancer. Today, patient advocates are transforming clinical trials by bringing the real-world experiences of patients directly to researchers. By acting as a bridge between science and the community, patient advocates boost enrollment in clinical trials, and help build a lasting trust Today we are speaking with Dr. Lior Braunstein, a radiation oncologist and researcher at Memorial Sloan Kettering Cancer Center, and Dr. Ellen Landsberger, a retired OB-GYN and patient advocate, also at Memorial Sloan Kettering Cancer Center. Together they are working on the ARCHER clinical trial, a study that is investigating a new treatment strategy for HER2-positive metastatic breast cancer. We'll talk about what they are hoping to accomplish through the ARCHER trial, what their collaborative process looks like and how patient advocates in clinical trials can help improve patient outcomes. Key Takeaways: Patient advocates help design better clinical trials The ARCHER trial aims to improve treatment outcomes Patient voices shape research from the very beginning Clinical trials study both treatment and quality of life Better access helps more patients join clinical trials Chapters 00:00:00 – Why patient advocates belong at the clinical trial design table 00:04:44 – From breast cancer survivor to patient advocate 00:07:46 – How advocates shape research and address patient concerns 00:12:08 – Inside the ARCHER trial and its goal to improve metastatic breast cancer treatment 00:19:03 – Measuring quality of life and improving access to clinical trials 00:26:28 – How patients can become advocates and influence future research

PeerView Family Medicine & General Practice CME/CNE/CPE Video Podcast
This content has been developed for healthcare professionals only. Patients who seek health information should consult with their physician or relevant patient advocacy groups.For the full presentation, downloadable Practice Aids, slides, and complete CME information, and to apply for credit, please visit us at PeerView.com/FJQ865. CME credit will be available until June 24, 2027.New Kids on the Block in Pretreated Metastatic EGFRm NSCLC: Emerging Strategies to Overcome Resistance In support of improving patient care, PVI, PeerView Institute for Medical Education, is jointly accredited by the Accreditation Council for Continuing Medical Education (ACCME), the Accreditation Council for Pharmacy Education (ACPE), and the American Nurses Credentialing Center (ANCC), to provide continuing education for the healthcare team.SupportThis activity is supported by an independent educational grant from AstraZeneca.Disclosure information is available at the beginning of the video presentation.

This content has been developed for healthcare professionals only. Patients who seek health information should consult with their physician or relevant patient advocacy groups.For the full presentation, downloadable Practice Aids, slides, and complete CME information, and to apply for credit, please visit us at PeerView.com/FJQ865. CME credit will be available until June 24, 2027.New Kids on the Block in Pretreated Metastatic EGFRm NSCLC: Emerging Strategies to Overcome Resistance In support of improving patient care, PVI, PeerView Institute for Medical Education, is jointly accredited by the Accreditation Council for Continuing Medical Education (ACCME), the Accreditation Council for Pharmacy Education (ACPE), and the American Nurses Credentialing Center (ANCC), to provide continuing education for the healthcare team.SupportThis activity is supported by an independent educational grant from AstraZeneca.Disclosure information is available at the beginning of the video presentation.
This content has been developed for healthcare professionals only. Patients who seek health information should consult with their physician or relevant patient advocacy groups.For the full presentation, downloadable Practice Aids, slides, and complete CME information, and to apply for credit, please visit us at PeerView.com/FJQ865. CME credit will be available until June 24, 2027.New Kids on the Block in Pretreated Metastatic EGFRm NSCLC: Emerging Strategies to Overcome Resistance In support of improving patient care, PVI, PeerView Institute for Medical Education, is jointly accredited by the Accreditation Council for Continuing Medical Education (ACCME), the Accreditation Council for Pharmacy Education (ACPE), and the American Nurses Credentialing Center (ANCC), to provide continuing education for the healthcare team.SupportThis activity is supported by an independent educational grant from AstraZeneca.Disclosure information is available at the beginning of the video presentation.
This content has been developed for healthcare professionals only. Patients who seek health information should consult with their physician or relevant patient advocacy groups.For the full presentation, downloadable Practice Aids, slides, and complete CME information, and to apply for credit, please visit us at PeerView.com/FJQ865. CME credit will be available until June 24, 2027.New Kids on the Block in Pretreated Metastatic EGFRm NSCLC: Emerging Strategies to Overcome Resistance In support of improving patient care, PVI, PeerView Institute for Medical Education, is jointly accredited by the Accreditation Council for Continuing Medical Education (ACCME), the Accreditation Council for Pharmacy Education (ACPE), and the American Nurses Credentialing Center (ANCC), to provide continuing education for the healthcare team.SupportThis activity is supported by an independent educational grant from AstraZeneca.Disclosure information is available at the beginning of the video presentation.
This content has been developed for healthcare professionals only. Patients who seek health information should consult with their physician or relevant patient advocacy groups.For the full presentation, downloadable Practice Aids, slides, and complete CME information, and to apply for credit, please visit us at PeerView.com/FJQ865. CME credit will be available until June 24, 2027.New Kids on the Block in Pretreated Metastatic EGFRm NSCLC: Emerging Strategies to Overcome Resistance In support of improving patient care, PVI, PeerView Institute for Medical Education, is jointly accredited by the Accreditation Council for Continuing Medical Education (ACCME), the Accreditation Council for Pharmacy Education (ACPE), and the American Nurses Credentialing Center (ANCC), to provide continuing education for the healthcare team.SupportThis activity is supported by an independent educational grant from AstraZeneca.Disclosure information is available at the beginning of the video presentation.
This content has been developed for healthcare professionals only. Patients who seek health information should consult with their physician or relevant patient advocacy groups.For the full presentation, downloadable Practice Aids, slides, and complete CME information, and to apply for credit, please visit us at PeerView.com/FJQ865. CME credit will be available until June 24, 2027.New Kids on the Block in Pretreated Metastatic EGFRm NSCLC: Emerging Strategies to Overcome Resistance In support of improving patient care, PVI, PeerView Institute for Medical Education, is jointly accredited by the Accreditation Council for Continuing Medical Education (ACCME), the Accreditation Council for Pharmacy Education (ACPE), and the American Nurses Credentialing Center (ANCC), to provide continuing education for the healthcare team.SupportThis activity is supported by an independent educational grant from AstraZeneca.Disclosure information is available at the beginning of the video presentation.
This content has been developed for healthcare professionals only. Patients who seek health information should consult with their physician or relevant patient advocacy groups.For the full presentation, downloadable Practice Aids, slides, and complete CME information, and to apply for credit, please visit us at PeerView.com/FJQ865. CME credit will be available until June 24, 2027.New Kids on the Block in Pretreated Metastatic EGFRm NSCLC: Emerging Strategies to Overcome Resistance In support of improving patient care, PVI, PeerView Institute for Medical Education, is jointly accredited by the Accreditation Council for Continuing Medical Education (ACCME), the Accreditation Council for Pharmacy Education (ACPE), and the American Nurses Credentialing Center (ANCC), to provide continuing education for the healthcare team.SupportThis activity is supported by an independent educational grant from AstraZeneca.Disclosure information is available at the beginning of the video presentation.
This content has been developed for healthcare professionals only. Patients who seek health information should consult with their physician or relevant patient advocacy groups.For the full presentation, downloadable Practice Aids, slides, and complete CME/MOC/AAPA/IPCE information, and to apply for credit, please visit us at PeerView.com/QSQ865. CME/MOC/AAPA/IPCE credit will be available until June 29, 2027.Innovation Takes the Stage in HNSCC: Immunotherapy and Novel Therapeutics in Locally Advanced and Recurrent/Metastatic Disease In support of improving patient care, this activity has been planned and implemented by PVI, PeerView Institute for Medical Education, and Head and Neck Cancer Alliance. PVI, PeerView Institute for Medical Education, is jointly accredited by the Accreditation Council for Continuing Medical Education (ACCME), the Accreditation Council for Pharmacy Education (ACPE), and the American Nurses Credentialing Center (ANCC), to provide continuing education for the healthcare team.SupportThis activity is supported through independent educational grants from AstraZeneca, AVEO Pharmaceuticals, Inc., Johnson & Johnson, and Merck & Co., Inc., Rahway, NJ, USA.Disclosure information is available at the beginning of the video presentation.
This content has been developed for healthcare professionals only. Patients who seek health information should consult with their physician or relevant patient advocacy groups.For the full presentation, downloadable Practice Aids, slides, and complete CME/MOC/AAPA/IPCE information, and to apply for credit, please visit us at PeerView.com/QSQ865. CME/MOC/AAPA/IPCE credit will be available until June 29, 2027.Innovation Takes the Stage in HNSCC: Immunotherapy and Novel Therapeutics in Locally Advanced and Recurrent/Metastatic Disease In support of improving patient care, this activity has been planned and implemented by PVI, PeerView Institute for Medical Education, and Head and Neck Cancer Alliance. PVI, PeerView Institute for Medical Education, is jointly accredited by the Accreditation Council for Continuing Medical Education (ACCME), the Accreditation Council for Pharmacy Education (ACPE), and the American Nurses Credentialing Center (ANCC), to provide continuing education for the healthcare team.SupportThis activity is supported through independent educational grants from AstraZeneca, AVEO Pharmaceuticals, Inc., Johnson & Johnson, and Merck & Co., Inc., Rahway, NJ, USA.Disclosure information is available at the beginning of the video presentation.
At just 32 years old, Keisha Kinison was working in women's health when she suddenly found herself as the patient. In this episode, we'll talk about what it was like to discover her diagnosis before a physician had the chance to call, why she made the difficult decision to change doctors during treatment, how her experience transformed her and the incredible support that helped carry her through. Woven throughout every chapter of her story is one powerful message: trust yourself, advocate for yourself, and never be afraid to seek the care you deserve. Key takeaways: Breast cancer can happen at a young age Self-advocacy is essential A strong support system makes a difference Treatment can involve unexpected setbacks Know your body and don't ignore changes Chapters 00:00 Keisha's breast cancer diagnosis at age 32 01:52 Testing, imaging, and receiving the diagnosis 05:12 Triple-negative breast cancer and treatment challenges 09:15 Advocating for herself and changing oncologists 12:11 The support that carried her through treatment 15:33 How cancer changed her career and advice for others Learn more at realpink.komen.org and komen.org Real Pink, by Susan G. Komen, shares real stories and expert insights to support people navigating breast cancer, from diagnosis through survivorship.
There is a lot of conversation right now about funding for cancer research and possible cuts to research projects that will improve our understanding and treatment of breast cancer. I'm pleased to be joined today by two researchers who are sharing their perspectives on the inextricable link between grant funding and sustained research. Dr. Benjamin Schrank is an Assistant Professor in the Department of Radiation Oncology at The University of Texas MD Anderson Cancer Center, and Dr. Donald McDonnell is the Glaxo-Wellcome Distinguished Professor of Molecular Cancer Biology at Duke University School of Medicine. Dr. McDonnell is a well-established researcher whose work focuses on developing new drugs to treat metastatic breast cancer. Dr. Schrank is early in his research career and focused on harnessing the body's immune system to improve response to treatments for metastatic breast cancer. Both recently received research grants from Susan G. Komen to support their innovative work that will help improve breast cancer care and patient outcomes. Key Takeaways: Breakthrough cancer treatments can take decades to develop Fundamental research is the foundation of future therapies Early-stage funding is critical for innovation Research funding directly impacts patients Chapters 00:00 Introduction 01:40 Meet the researchers and their current projects 03:45 Why medical breakthroughs take decades to achieve 11:15 The critical role of grant funding in scientific research 20:20 Supporting the next generation of cancer researchers Learn more at realpink.komen.org and komen.org Real Pink, by Susan G. Komen, shares real stories and expert insights to support people navigating breast cancer, from diagnosis through survivorship.
Featuring perspectives from Dr Kevin Punie and Dr Tiffany A Traina, including the following topics: Introduction: Where We Are; Where We're Heading (0:00) First-Line Treatment of BRCA Wild-Type Disease (9:14) First-Line Treatment of BRCA-Mutant Disease (38:48) Novel Approaches (47:49) CME information and select publications
Welcome to the Komen Health Equity Revolution series on Real Pink — where patients, advocates, researchers and community partners come together to talk honestly about what's standing in the way of breast health equity, and what we're doing to change it. June is Pride Month — a time to celebrate identity, community and the courage it takes to live authentically. Today's conversation sits right at the heart of that. Because advocating for yourself, knowing your body and refusing to be dismissed, that's not just a health message. That's a love letter to who you are. Our guest today is Shelby Smith. She was 30 years old when she noticed something felt off. No family history of breast cancer. Young, healthy, going about her life as a wife and mom to a 7-year-old daughter. But she trusted herself — and that decision changed everything. Shelby faced a 12-centimeter tumor, a bilateral mastectomy, 16 rounds of chemo and 15 rounds of radiation. She did her own research, built her own notebook, asked her own questions — and came out the other side with a message she wants every young woman to hear: Know your normal. And when something doesn't feel right, advocate for yourself. Key Takeaways: Trust your instincts when something feels off Self-advocacy can change outcomes Being informed helps patients navigate treatment Cancer can affect more than physical health Including loved ones in the journey matters Chapters 00:00 Introduction: Shelby's Breast Cancer Story 02:07 Discovering a Lump and Seeking Answers 04:37 Diagnosis, Testing, and Receiving the News 10:07 Research, Self-Advocacy, and Navigating Treatment 17:33 Identity, Family, and Talking to Her Daughter 24:46 Life After Treatment and Advice for Young Women Learn more at realpink.komen.org and komen.org Real Pink, by Susan G. Komen, shares real stories and expert insights to support people navigating breast cancer, from diagnosis through survivorship.
A breast cancer diagnosis may feel like it changes your entire life in an instant, but it doesn't get to define who you are or make all your choices for you. On today's episode of Real Pink, we're joined by Amanda Sangemino, a remarkable young woman whose diagnosis came at an age when cancer was likely the last thing on her mind. What began with a concern that was initially dismissed ultimately led her to trust her instincts, advocate for herself, and make a series of personal decisions about her treatment and future. Throughout the process, she was determined not to let fear and cancer make every decision for her. Today, she'll talk about the choices that she made about fertility, surgical options and maintaining an active lifestyle and why trusting yourself can be one of the most powerful tools you have. Key Takeaways: Mindset can play a powerful role during treatment Trust your instincts and advocate for yourself Maintaining normalcy can be empowering Don't let cancer make every decision for you A strong support system makes a difference Chapters: 00:00 – Amanda's Breast Cancer Story Begins 01:28 – Finding a Lump and Receiving a Misdiagnosis 04:22 – Seeking a Second Opinion and Getting Answers 07:00 – Why Self-Advocacy Matters for Young Women 10:00 – Fertility, Menopause, and Treatment Decisions 14:43 – Choosing Surgery, Staying Active, and Building Support 23:09 – Amanda's Final Advice Learn more at realpink.komen.org and komen.org Real Pink, by Susan G. Komen, shares real stories and expert insights to support people navigating breast cancer, from diagnosis through survivorship.
Can you really treat prostate cancer effectively without knowing the genetics? In this episode of BackTable Urology, Dr. Evan Yu and Dr. Tanya Dorff join host Dr. Alan Tan to discuss why genetic testing is essential in personalized prostate cancer care. They discuss when and how to perform germline and somatic testing, address common barriers, and share best practices for counseling patients. --- Get the BackTable apphttps://www.backtable.com/app --- This podcast is supported by an educational grant from Pfizer. --- Timestamps 00:00 - Introduction02:18 - Who Gets Somatic Testing?06:43 - Patient Barriers to Testing09:00 - Genetic Testing Workflow12:28 - Treating BRCA2 Alterations24:18 - Monitoring Progression: ctDNA vs. PSA vs. Imaging29:32 - Treating mCRPC with ATM Mutations34:39 - CDK12 Classification 37:43 - Closing Takeaways --- More about this episode The doctors explore how BRCA2 and other DNA repair alterations can directly shape treatment decisions, focusing on the roles of PARP inhibitors and platinum therapy in advanced cases. The discussion highlights why both germline and somatic testing are critical for identifying actionable mutations and discuss the nuances of interpreting test results, including current limitations and emerging biomarkers. They also examine challenges such as insurance coverage, patient misconceptions, and workflow integration, as well as the movement toward truly personalized, biology-driven approaches in prostate cancer care. --- Resources Niraparib and abiraterone acetate plus prednisone for HRR-deficient metastatic castration-sensitive prostate cancer: a randomized phase 3 trial:https://pmc.ncbi.nlm.nih.gov/articles/PMC12705445/ Capivasertib plus abiraterone in PTEN-deficient metastatic hormone-sensitive prostate cancer: CAPItello-281 phase III study:https://www.annalsofoncology.org/article/S0923-7534(25)04936-1/fulltext Apalutamide for Metastatic, Castration-Sensitive Prostate Cancer:https://www.nejm.org/doi/full/10.1056/NEJMoa1903307 ARCHES 5-year Survival with Enzalutamide Plus Androgen-deprivation Therapy in Metastatic Hormone-sensitive Prostate Cancer Patientshttps://www.sciencedirect.com/science/article/pii/S0302283825048766 First-Line Camizestrant for Emerging ESR1-Mutated Advanced Breast Cancer:https://www.nejm.org/doi/abs/10.1056/NEJMoa2502929 PROMISE Registry:https://www.prostatecancerpromise.org/ Talazoparib plus enzalutamide in men with HRR-deficient metastatic castration-resistant prostate cancer: final overall survival results from the randomised, placebo-controlled, phase 3 TALAPRO-2 trial:https://www.thelancet.com/journals/lancet/article/PIIS0140-6736(25)00683-X/abstract --- BackTable Urology is the go-to podcast for urologists, urologic oncologists, and urogynecologists. Download the free BackTable app to get early access to new episodes, cases, and courses curated by physicians in your specialty. ► https://www.backtable.com/app
Today on National Cancer Survivor's Day, we're joined by a remarkable performer whose strength, vulnerability, and resilience have inspired millions around the world. She has taken the stage as a backup vocalist for numerous top artists and most recently dazzled the crowds on the biggest tour in music history with global superstar Taylor Swift. However, audiences were moved even more deeply when she chose to publicly share something far more personal – her breast cancer journey. After Jeslyn Gorman's diagnosis become known through The Eras Tour docuseries, fans witnessed the emotional reality of navigating cancer while stepping away from a career and community she loves so deeply. From continuing to tour in the early days of diagnosis, to facing treatment side effects and returning to the stage immediately following treatment, her story is one of courage, grace and resilience. Today, Jeslyn opens up about the support she received, what survivorship looks like now and most importantly, shares an empowering message for young women about listening to their bodies, advocating for their health, and never underestimating the importance of early detection. Key Takeaways: Early detection can save lives. You can experience joy and fear at the same time. A strong support system makes a major difference. Recovery is gradual and requires patience. Cancer changes your life, but it doesn't define it. Chapters 00:00 – Jeslyn's Breast Cancer Diagnosis 05:24 – Continuing to Perform After Diagnosis 07:38 – Going Public With Her Cancer Story 13:22 – Breast Health and Self-Advocacy 18:07 – Support From Family, Friends, and the Tour Community 22:17 – Staying Positive During Treatment 25:17 – Chemotherapy and Physical Recovery 31:49 – Hair Loss and Identity Learn more at realpink.komen.org and komen.org Real Pink, by Susan G. Komen, shares real stories and expert insights to support people navigating breast cancer, from diagnosis through survivorship. 37:29 – Life After Treatment and Survivorship
© 2020-2026 Ivy Podcast Discovery LLC
